SAQ 1
A 24 year old obese female presents with a deliberate overdose after a relationship breakdown. She took 60 x 200mg ibuprofen tablets, 30 x 50 mg sertraline tablets, 20 x 10 mg olanzapine tablets, and 10 x 10mg of diazepam approximately an hour before presenting.
On arrival, her BP is 190/110, HR 90, T 38°C, RR 24. She is GCS 15/15.
- List two specific toxidromes you may expect to see in this patient. Briefly state two examination findings that may differentiate between the toxidromes. (4 marks)
- Serotonin syndrome – CLONUS/HYPERREFLEXIA, agitation – coma
- Neuroleptic malignant syndrome – higher temperature than SS, rhabdomyolysis, bradyreflexia
- List four blood tests you will order for this patient and justify each. (4 marks)
- *BHCG – confirm pregnancy – high BP may be pre-eclampsia
- *CK – confirm rhabdomyolysis
- VBG – metabolic acidosis secondary to ibuprofen
- Paracetamol level – exclude paracetamol as co-ingestant
- Blood tests for the patient are shown. Soon after receiving these, the patient seizes. State your management of her seizure in order, with doses where appropriate. End points are not necessary, as we assume we will cease medication when the seizures stop. (2 marks)
- *Eclampsia – give MgSO4 4g IV over 10 mins.
- Benzodiazepines – diazepam 10mg reasonable second line.
Na 132
K 4.2
Cl 99
HCO3 24
Glu 18
Urea 6
Creatinine 86
Paracetamol <20
Bili 3
GGT 70
ALP 76
ALT 60
AST 75
Lipase 20
CK 2008
BHCG 1300
SAQ 2
A 78 year old male from a low level care nursing home is brought in by ambulance with delirium. The nursing home letter states he has been increasingly agitated over the past few days, despite increasing doses of olanzapine and haloperidol for behavioural control. His past history is significant for hayfever, Parkinsons disease, depression, and urinary incontinence. His medications include antihistamines, oxybutynin, amantadine, and amitriptyline.
His BP is 90/62, HR 140bpm regular, T 38°C. His skin is flushed and warm; his pupils are dilated.a. List
- List four differential diagnoses for the patient’s presentation. (4 marks)
- *Sepsis – encephalitis/meningitis, other
- *Anticholinergic syndrome
- Other infections…..Hypoglycaemia…usual differential for hot, agitated patients.
- You examine the patient, finding no abnormalities except for a palpable, non-tender bladder. The patient is mumbling incoherently, and has to be restrained by his nurse as he leans over the bed to “pick things up off the floor”. State the most likely diagnosis for this patient and a reasonable cause. (2 marks)
- Anticholinergic syndrome – agitated, confused, picking things, mydriasis. Cause – multiple medications that can cause it – in fact, all of the ones listed!!
- Outline your management of this patient.
- Sedation with benzodiazepines – diazepam or similar
- IDC for urinary retention
- IVT/supportive as patient unlikely to have been drinking/eating
- Cease offending medications
- Feed back to nursing home re over-use of medications
- After sedating the patient with 20mg of diazepam, he remains agitated. State a medication you may consider giving him, including a possible side effect of this medication. (2 marks)
- Physostigmine – a reversible AchE inhibitor. Indicated in severe anticholinergic delirium unresponsive to benzodiazepine sedation, or in poisoning with a pure anticholinergic agent. Possible side effect is over-effect – ie creation of a cholinergic syndrome!
SAQ 3
A normally healthy 23 year old student presents with abdominal pain and vomiting. He has no past history apart from migraines, which have been increasingly frequent over the past few weeks, a fact he attributes to his upcoming exams. His BP is 120/70, HR 120, RR 30, sats 100% RA. He is triaged to the resuscitation area and a VBG taken.
pH 7.58
PCO2 21
PO2 154
HCO3 19
Na 127
K 5.2
Cl 79
- Describe the blood gas and list two differential diagnoses for this patient based on your results. (3 marks)
- Triple disturbance – respiratory alkalosis, HAGMA, metabolic alkalosis.
- DDx: sepsis, salicylate toxicity
- On further questioning, the patient states he has increased his aspirin use due to his headaches, and has been using oil of wintergreen for sore muscles. Complete the following table regarding risk assessment in salicylate toxicity. (4 marks)
| Aspirin dose mg/kg | Effect |
| <150 | Minimal |
| 150-300 | Mild to moderate. Tinnitus, vomiting, hyperpnoea |
| 300 | Severe intoxication. Met acidosis, altered GCS, seizures |
| 500 | Potentially lethal |
- Briefly describe the underlying mechanism for each of the disturbances seen on the blood gas in aspirin toxicity. (3 marks)
Respiratory alkalosis – stimulation of the respiratory system directly
Metabolic acidosis – lactic acid builds up due to uncoupled oxidative phosphorylation
Metabolic alkalosis – vomiting due to irritant effect of aspirin - What is a bezoar and how does it affect management of aspirin overdose? (2 marks)
- Bezoar – solid mass of indigestible material, often forms in aspirin overdose, reducing removal/absorption of aspirin and prolonging toxic effect. May need MDAC to counter effect of bezoar.
- What are the indications for haemodialysis in aspirin overdose? (3 marks)
- Unable to alkalinise urine
- Increasing salicylate levels despite urinary alkalinisation
- Severe toxicity – altered mentation, acidemia, renal failure
- Very high salicylate levels
SAQ 4
A 46 year old male metal worker presents to ED with burns to his left hand and forearm. He states he was using an etching material at work when it spilt over his arm. The MSDS for the substance identifies it as hydrofluoric acid. He is in significant pain and has not applied first aid. He is also concerned he may have inhaled some of the vapours and complains of chest pain.
- What is the toxic mechanism involved in hydrofluoric acid burns? (2 marks)
- Binds Calcium and Magnesium – causing cell dysfunction and death. Acts like an alkali rather than an acid.
- An ECG is taken. What is the major abnormality shown on the ECG, and what does this signify? (2 marks)
- Prolonged QTc interval. Signifies hypocalcaemia.
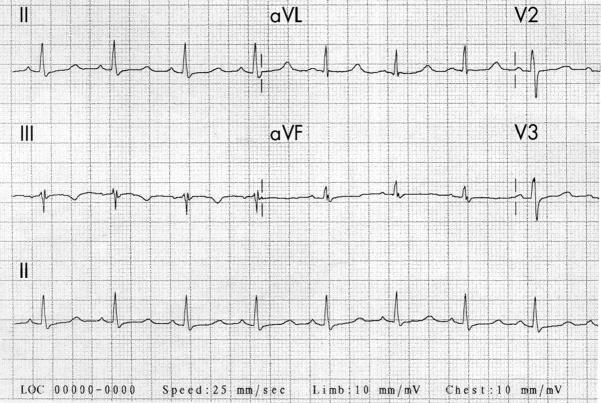
- The patient remains in significant pain. Apart from standard pain medications, list four treatment options for this patient, including route of administration. (4 marks)
- IV calcium gluconate 10% – 60ml over 5 mins
- Intradermal/intraarterial calcium gluconate – 1amp in 40ml NS
- Calcium paste 2.5%/Mylanta paste in glove
- Nebulised calcium gluconate
- State your disposition for this patient, with justification. (1 mark)
- Burns unit – hand burn and chemical burn. Both indications for burns unit transfer.
- For alkalis and acids, state the type of necrosis seen in toxicity. (2 marks)
Alkali – liquefactive necrosis
Acid – coagulative necrosis
SAQ 5
A 6 year old boy is brought in by ambulance. His mother states he and his brother were swimming in the family pool when the child started screaming. He then vomited and collapsed. Examination reveals an unconscious child with significant salivation and diaphoresis.
- What is the likely toxicological cause of his presentation? (1 mark)
- Funnel web spider bite
- For each of the following systems, list three symptoms you may see in this envenomation. (4 marks)
| System | Symptoms |
| Cardiovascular | Hypotension, bradycardia, tachycardia, hypertension, APO |
| Autonomic | Sweating, salivation, piloerection, lacrimation |
| CNS | Fasciculation, spasms, coma, paraesthesia oral |
| General | Abdominal pain, vomiting, agitation, headache |
- Soon after arrival, the child arrests. Outline your actions now. (3 marks)
- Four ampoules of antivenom IV push – indicated in cardiac arrest
- Standard APLS protocol – CPR with 30:2 etc
- Atropine for secretions
SAQ 6
An 18 year old female is brought in by friends from a Rave party. They state she had been dancing for several hours when she collapsed and had a seizure lasting 3 minutes. Her core temperature is 39C. She is taken to resuscitation and VBG taken (shown).
pH 7.45
PCO2 21
HCO3 24
Na 112
K 5.2
Cl 79
Urea 8
Glucose 9
- Describe the VBG and give a likely cause of the major abnormality shown. (2 marks)
- Respiratory alkalosis (hyperventilation) with normal AG. Significant hyponatremia with low osmolality.
- Ecstasy overdose with SIADH related hyponatremia.
- State 5 differential diagnoses for her presentation. (5 marks)
- Ecstasy, epilepsy, meningitis/encephalitis, drug intoxication, etc etc.
- Outline your treatment of this patient. (3 marks)
- 3% NS 100ml stat, repeat until Na >120.
- Fluid restriction for SIADH.
- Diazepam for seizures.
- Cooling as needed.
- Her blood tests return a CK of 20,500. Briefly describe your disposition of this patient and justify. (2 marks)
- ICU – patient needs dialysis, as she cannot be fluid treated for rhabdomyolysis given her SIADH. Dialysis probably best option.

