SAQ 1
- List five diagnostic criteria for Kawasaki Disease (KD) in a 4 year old boy with fever.
- High fever > 5 days
- Bilateral non-exudative conuunctivitis
- Skin changes – oedema, desquamation
- Cervical LAN
- Polymorphous rash
- Strawberry tongue
- All diagnostic criteria for KD are met in this patient. List and justify 3 investigations in this child.
- ECHO – cardiac involvement
- ASOT/Anti DNAase B
- Platelet count (marked thrombocytosis common in 2nd week illness)
- List three possible treatment options for KD in this patient.
- High dose aspirin 3-5 mg/kg
- IV steroids
- IV Ig
SAQ 2
A 3-month-old girl is brought into ED with pallor and lethargy for the past hour. She has had fevers and URTI symptoms for the past 3 days. Her observations are as follows:
GCS 15/15 but floppy/lethargic
HR 220
BP 75/45
CRT 2 seconds
Sats 95% RA
Temp 38.2 C
This is her ECG.
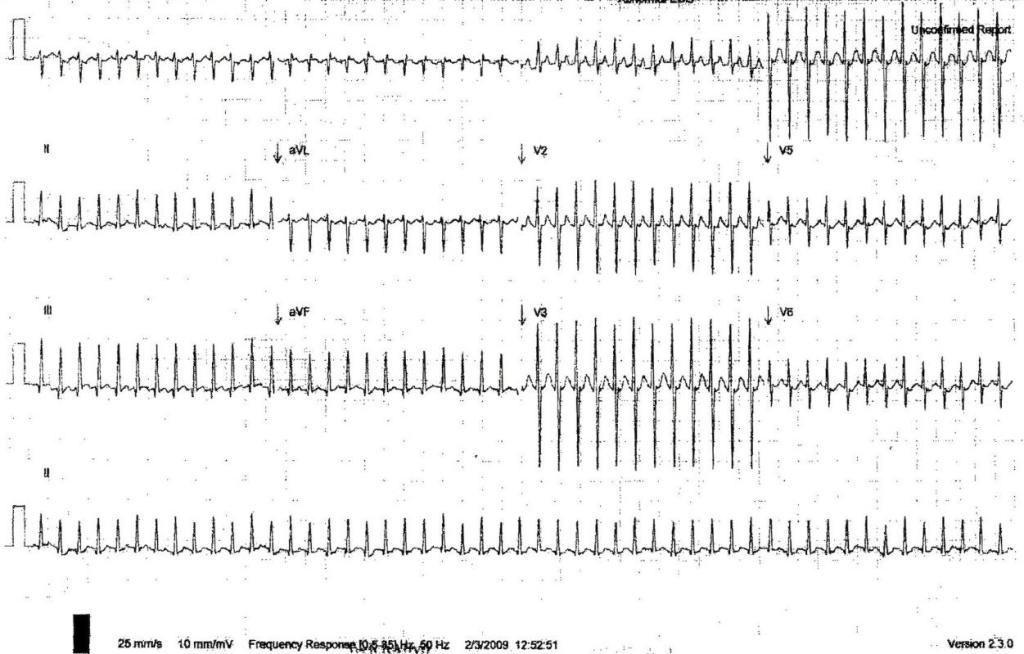
- What is the most likely diagnosis?
- SVT
- What are two features of the ECG that support this diagnosis?
- Rate > 150bpm
- No P waves visible
- Narrow complex tachycardia
- List 3 treatment options in the order of escalation that you would perform them.
- Ice on face
- Adenosine 100mcg/kg, then 200mcg/kg, then 300mcg/kg
- DC cardioversion
- List 4 investigations you would perform in the ED with a justification.
- CXR – cardiomegaly, DCM secondary to viral illness
- BSL
- Septic screen (FBE, EUC, Urine dip) – to exclude sepsis/infection as cause of SVT
SAQ 3
A 4 year old girl presents with anaphylaxis after a bee sting. She is poorly responsive, pale and floppy. She has no stridor but widespread wheeze on chest auscultation.
Her observations are: HR 152, BP 68/42, RR 56, T 37, Sats 92% on 10L oxygen.
- List five immediate steps in your management of this child, including doses where necessary.
- Move to resuscitation room, full monitoring
- Remove beesting
- Lie child down (hypotensive), consider raising legs
- IM adrenaline 150mcg into lateral thigh (0.01ml/kg of 1:1000)
- Fluid bolus 20ml/kg Normal saline – aim BP > 90mmHg
- Hydrocortisone 4mg/kg IV
- The child remains poorly responsive after these measures and you decide to intubate. What two sizes of ETT will you prepare for intubation?
- ETT = age/4+ 4 = 5, 4.5 (one size smaller due to likely oedema airway)
- Her BP remains low post-intubation and two fluid boluses and her peripheries are cold. What inotrope will you use and why? Give dose.
- Adrenaline 0.1mcg/kg/min – combined inotropic effect and anaphylaxis treatment. Child is in cold shock, so noradrenaline not indicated.
SAQ 4
A 4 week old child is brought to ED by his concerned parents with four hours of increasing breathing difficulty. He has a four day history of increased cough and conjunctivitis. On arrival, he is triaged to resus, IV access obtained and monitored. He is mottled and lethargic. His obs are: HR 180bpm, RR 65, T 37.9 (axilla), and sats unmeasurable due to poor trace. BGL is 5.4mmol/L.
- List 8 differential diagnoses you would consider in this child’s presentation.
- Trauma
- Heart disease
- Electrolyte disturbance
- Metabolic disturbance
- Inborn error of metabolism
- Sepsis
- Formula dilution/overconcentration
- Intestinal catastrophe/intussusception
- Toxins
- Seizures/CNS
- NAI
Fail question if say DKA – BGL normal. Unlikely NAI, as parents concerned.
- List three initial steps in your resuscitation of this child with justification.
- Oxygen to keep sats >94%
- Fluid bolus – 20ml/kg of NS
- Empiric antibiotics – cefotaxime 50mg/kg
SAQ 5
A 3 year old boy is brought in by his mother refusing to weight bear on his right leg. His mother says he started limping 3 days ago and now will not walk. The child appears otherwise well and has no past medical history.
- Fill out the following table regarding differential diagnosis of the limping child.
| Diagnosis | Cause | Findings on clinical exam/posture | Typical age onset | Risk factors |
| Septic join | Bacterial – staph/strep | Extremely limited ROM | Any | Diabetes |
| Transient synovitis | Recent viral illness | Leg held in flexion/abduction | 3-8 yrs | Nil |
| Perthes | Avascular necrosis | Limited int rotation and abduction. May be shortened leg. | 2-12 yrs | Low birth weight Male |
| SCFE* | Mechanical slippage of epiphysis | Externally rotated and shortened | 10-14 yrs | Obesity Renal/thyroid issues |
SCFE – slipped capital femoral epiphysis
- Give three tests you would order in this child and justify.
- FBE/CRP – to exclude septic arthritis
- X ray – to exclude fracture/Perthes
- Ultrasound – to exclude effusion/infection, but rarely used
- CT/MRI – to exclude septic joint/occult fracture
- Bone scan – to exclude SCFE, septic joint, Perthes
SAQ 6
A 6 year old presents after running into a coffee table, sustaining a laceration above her right eyebrow. There was no loss of consciousness and no other injury. The wound needs sutures. Complete the following table of anaesthetic options in this child (one example per box).
| Medication | Dose/route | Advantage | Disadvantage |
| Midazolam | PO/IV/IN 0.2mg/kg | Anxiolytic | No analgesia |
| Ketamine | IV 1.5mg/kg | Rapid onset | Vomiting/salivation |
| Propofol | IV 1-2 mg/kg | Rapid onset | No analgesia |
| Nitrous oxide | 30-50% inh | Rapid on/off | Vomiting |
| Fentanyl | IN 1.5mg/kg | Analgesia | Respiratory depression |
SAQ 7
A 6 year old child with no significant PMHx presents with abdominal pain and vomiting. Her observations are BP 74/45, HR 158 bpm, RR 50, T 37, Sats 100% RA.
- Give three differential diagnoses for this presentation.
- DKA
- Sepsis (less likely given afebrile)
- Addisons/other metabolic
- Poisoning
- Intestinal catastrophe
- Her BGL is “high” and ketones are present in her urine. List your management of her DKA, giving doses and endpoints where appropriate.
- Volume resuscitation – 20mlkg NS bolus stat, then correct remaining fluid deficit over 48 hours
Change from NS to 4% and 1/5 once BGL <15 - Insulin infusion – 0.1units/kg/hr. Reduce to 0.05units/kg/hr once BGL < 12
- K+ replacement – aim K+>4. Add K+ to bags of NS at rate of 10-20mmol/hr once K+<5
- Volume resuscitation – 20mlkg NS bolus stat, then correct remaining fluid deficit over 48 hours
SAQ 8
A 5 year old boy is brought to your major referral ED by his mother, who states he was bitten on his ankle by a snake an hour ago. He has a pressure immobilisation bandage in place. He is currently asymptomatic with stable vitals.
- Give four features on assessment that would indicate envenomation?
- Early collapse suggests serious envenomation (likely brown snake)
- Evidence of bleeding – cannula/bite site, GI, etc
- Neuro symptoms – respiratory weakness, ptosis, CN involvement
- Fang marks, local necrosis/bruising
- N/V/headache/respiratory distress
- An hour later, the child remains asymptomatic. Initial investigations are normal. The PIB is removed. List the 3 criteria which need to be met for the child to be discharged.
- Repeat blood tests and neuro exam at 1 hour post PIB removal
- Repeat blood tests and neuro exam at 6 and 12 hours post bite
- If no evidence envenomation, can be discharged then.
- How many hours are considered adequate observation to ensure envenomation has not occurred in Australia?
- Most Australian snakes will show symptoms within 12 hours of bite.
SAQ 9
- List 6 medications/substances that are potentially lethal in children with only a small amount ingested?
- Sulfonylureas
- CCB
- Beta blockers
- Clonidine
- Opiates
- Oil of wintergreen
- Camphor
- TCA
- Eucalyptus oil
- A 2-year-old child presents after a suspected accidental drug ingestion. The child has been seizing for 10 minutes.
- A 2-year-old child presents after a suspected accidental drug ingestion. The child has been seizing for 10 minutes.
- Lorazepam 0.1mg/kg
- Phenytoin 20mg/kg over 20 minutes
- Give two medications that may be given with neither IV or IO access, with route of administration and dose.
- Midazolam (buccal) 0.5mg/kg
- Diazepam (rectal) 0.5mg/kg
- A 2-year-old child presents after a suspected accidental drug ingestion. The child has been seizing for 10 minutes.

