SAQ 1
A 6 year old child is brought to ED by her mother with nausea and vomiting. She had been seen in ED two days prior and treated for an acute exacerbation of asthma. The child is weak and pale, with a respiratory rate of 36/min and pulse rate of 140bpm. Skin turgor is poor. She is moved to a resuscitation room and IV access established. Her VBG is shown below.
pH 7.05
CO2 7
O2 28
HCO3 8
BE -20
Na 133
K 5.2
CL 98
BGL 28
- List four findings on the blood gas with a brief explanation for each. (4 marks)
- High anion gap metabolic acidosis (AG 15) – likely DKA given hyperglycaemia
- Inadequate compensation with respiratory alkalosis – hyperventilation
- Moderate hypokalaemia – expect K to be 5+0.5*3 = 6.5
- Delta ratio 0.93 – pure HAGMA, no evidence of NAGMA
*No points for Aa gradient, as question states this is a venous gas.
- Outline your management of this child in order, giving calculations and endpoints where appropriate. (8 marks)
- Estimated weight of child = ((age+4) 2) = 20kg
- Fluid resuscitation with NS – 20ml/kg bolus initially = 400ml stat
- Ongoing fluids: aim to correct remaining fluid deficit over 48 hrs. For example, 1 litre NS over one hour, then one litre over 2 hours. Change fluid to 4% and 1/5 once BGL <15.
- Aim HR<120, BP>90 (using formula age2+80 to estimate normal BP for age)
- K+ replacement – aim K+ of >4, add K to bags of NS at rate of 10-20mmol/hr once K is <5.0
- Insulin infusion – 0.1units/kg/hr. For this child, 0.6 units/hr of actrapid IV.
- Estimated weight of child = ((age+4) 2) = 20kg
- Three hours after initiating treatment, the child is haemodynamically stable. The nurse mentions to you that the child is now confused and complaining of a headache. Outline your diagnosis and management. (3 marks)
- Diagnosis: cerebral oedema. Brain reacts to DKA by producing osmoles to protect itself from shrinking. When DKA is corrected, an osmotic gradient causes fluid shift into the brain cells, causing oedema. Can be prevented by correcting fluid deficits over 48 hours.
- Management:
- *Mannitol 1g/kg IV.
- *Slow fluids down – fail question if not mentioned
- Diagnosis: cerebral oedema. Brain reacts to DKA by producing osmoles to protect itself from shrinking. When DKA is corrected, an osmotic gradient causes fluid shift into the brain cells, causing oedema. Can be prevented by correcting fluid deficits over 48 hours.
- Apart from the standard blood tests ordered in ED, state three blood tests you would consider ordering for this patient given this is her first presentation with this condition. (3 marks).
- Any of: Insulin antibodies, GAD antibodies (more in adults; tells whether DM1 or LADA), coeliac screen, TFTs, c peptide level.
SAQ 2
A 22 year old male with type 1 diabetes presents to ED with DKA. His BP is 80/40, HR 120bpm, and RR 24. He is afebrile and otherwise well.
- State three criteria for diagnosis of diabetes in a patient. (3 marks)
- Fasting BGL >7 on two separate occasions
- Random BGL >11 plus symptoms of hyperglycaemia (polyuria, polydipsia, etc)
- HbA1c level >6.5
- Briefly describe the two pathophysiological mechanisms causing his dehydration. (2 marks)
- Hyperglycaemia – osmotic diuresis in kidneys resulting in massive fluid loss
- Counterregulatory hormone glucagon – which leads to increased hyperglycaemia, therefore further diuresis
- List five precipitants of DKA in any diabetic patient. (5 marks)
- *Infection
- *Compliance issues
- Intoxication – alcohol, drugs
- Pregnancy
- Surgery/trauma
- CVA
- Steroids
- Blood tests reveal a HbA1C level of 9.6. What is the significance of this in this patient? (2 marks)
- HbA1c is a measure of average BGLs over the past 6-8 week period. It can be used as an indicator of diabetic control in patients with diagnosed diabetes. This is a high level, suggesting poor control.
- List four complications of DKA and how you will treat each. Doses are not required. (4 marks)
- Shock – adequate fluid resus then pressors/inotropes as needed
- Infection – empiric antibiotics if indicated
- *DVTPE – prophylaxis with clexane/heparin
- Cerebral oedema – cautious replacement of fluid deficit over 48 hrs
- Arrhythmia – potassium monitoring
- Stroke, ARDS, MI, Aspiration, other reasonable options.
SAQ 3
A 66 year old female from home is brought in by ambulance with decreased sensorium. She had been unwell for three days with abdominal pain, nausea, and vomiting. On arrival, her HR is 130, BP 90/40, T 37.4°C, and RR 18. Sats 99% on air. She has no regular medications except for frusemide and calcitonin. A fingerprick ketone test is negative. A VBG taken on arrival is shown.
pH 7.30
CO2 30
O2 27
HCO3 15
Na 155
K 3.3
CL 98
BGL 40
Urea 7
Creatinine 150
Lactate 6.2
- Describe the major abnormalities on the blood gas, giving the most likely diagnosis. (6 marks)
- High anion gap metabolic acidosis – likely due to lactate
- Respiratory alkalosis compensation – incomplete/inadequate
- Elevated serum osmolarity – 357 (hyperosmolar)
- Moderate hypokalaemia, should be higher given acidemia
- Significant hypernatremia
Likely diagnosis: HHNS – elevated BGL, elevated osmolarity, normal ketones.
- Complete the following table regarding differences between DKA and HHNS. (7 marks)
| DKA | HHNS | |
| Ketones present? | Yes | No |
| Length of prodrome | Short | Long |
| Mortality | Low | High |
| Deficit causing illness | Insulin deficit | Water deficit |
| Severity of fluid deficit | Moderate | Severe |
| Age of patient | Young patients | Older patients |
| Prevalence | Common | Uncommon |
- How does treatment of HHNS differ from DKA? (2 marks)
- Overall it doesn’t – the treatment is still volume, potassium, insulin. The difference is that HHNS patients are often significantly more fluid deplete – up to 20% TBW – so many require more fluid/inotropes/etc.
- Give a likely cause of her presenting complaint, based on the information given. (1 mark)
- Pancreatitis secondary to hypercalcaemia – on calcitonin/frusemide for this.
SAQ 4
A 63 year old male presents to ED with nausea, vomiting, and abdominal pain for three days. He denies ingestion of any toxins or drugs during that time and has had poor oral intake due to ongoing intractable nausea. His GCS is 15/15, BP 110/60, HR 90, T 35°C. Blood tests taken on arrival are shown.
pH 7.22
CO2 29
HCO3 11
Na 131
K 4.3
CL 90
BGL 7.1
Urea 7
Creatinine 90
Bili 23
GGT 85
ALP 150
ALT 60
AST 80
Lipase 50
Ketones
BHB:acetoacetate ratio
8:1
- List the major findings on the blood tests and give a likely diagnosis. (6 marks)
- High anion gap metabolic acidosis (AG 30) with respiratory alkalosis compensation.
- Mild hyponatremia.
- Normal renal function.
- LFTs consistent with chronic alcohol abuse (GGT elevated, AST>ALT)
- Normal serum osmolarity
Likely alcoholic ketoacidosis secondary to recent cessation of alcohol.
- State four treatments indicated for this patient (doses and endpoints not required). (4 marks)
- Thiamine 300mg IM/IV
- IVT – 4% and 1/5 NS
- Glucose supplementation to stimulate insulin production and stop ketone formation
- Consider Mg/Phosphate/MVT as patients often malnourished
*fail if suggest insulin – patient is euglycaemic, and insulin will precipitate hypoglycaemia and worsening ketoacidosis.
Bicarb is not indicated if pH>7.1
- Soon after commencing treatment, your intern tells you he accidentally gave the patient 15 units of actrapid. The patient now has a BGL of 2.0 and a decreased GCS. State a medication you will give the patient and justify your choice. (2 marks)
- Glucose – 25-50ml of 50% dextrose IV. Patient could be given glucagon, but given his alcohol abuse, he is likely to have poor liver function and low glycogen stores, so glucagon unlikely to work.
SAQ 5
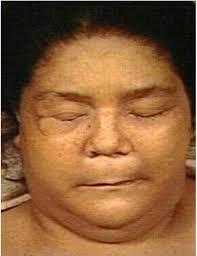
A 72 year old female is brought in by ambulance after concerned family members found her at home in a stuporous state. She has a past history of IHD, Coeliac disease, and bipolar disorder. Her regular medications are amiodarone and lithium. On arrival, she is moved to the resuscitation room. Her BP is 109/64, HR 46 sinus, T 31.2°C, and BGL 3.9. Her GCS is 10/15. Bloods taken on arrival are shown, as is an image of the patient.
pH 7.23
CO2 64
O2 71
Na 128
K 5
CL 90
BGL 3.9
Urea 7
Creatinine 150
- What is the likely diagnosis? (1 mark)
- Hypothyroidism/myxoedema coma secondary to lithium
- List four treatments indicated for this patient. Doses are not required. (4 marks)
- *Thyroid hormone replacement – preferably T4 given cardiac history
- Dextrose IVT for hypoglycaemia
- Water restriction for hyponatremia
- Passive rewarming for hypothermia
- Steroids/other reasonable options.
- The patient improves during a lengthy stay in AMU (after endocrine refused admission) and her lithium is ceased. Two weeks after discharge, she returns via ambulance with a complaint of agitation. Her BP is 210/100, HR 130, T 37.8°C, and RR 24. She denies intoxication or ingestion and has been complaint with her medications. List four medications you will give her in order of administration. Doses are not required, but desirable. (4 marks)
- Propothiouracil 900mg NG/PO
- Iodine – 5 drops Lugols iodine
- Propranolol 1-2mg IV up to max 10mg
- Hydrocortisone 200mg IV
- State two possible causes for her second presentation, with justification. (2 marks)
- Thyroxine overdose – worsening bipolar since cessation lithium, took too much
- Amiodarone – contains iodine, can precipitate thyroid storm

